

Moderna has successfully developed a cancer therapeutic mRNA vaccine against melanoma. Let's unpack that.
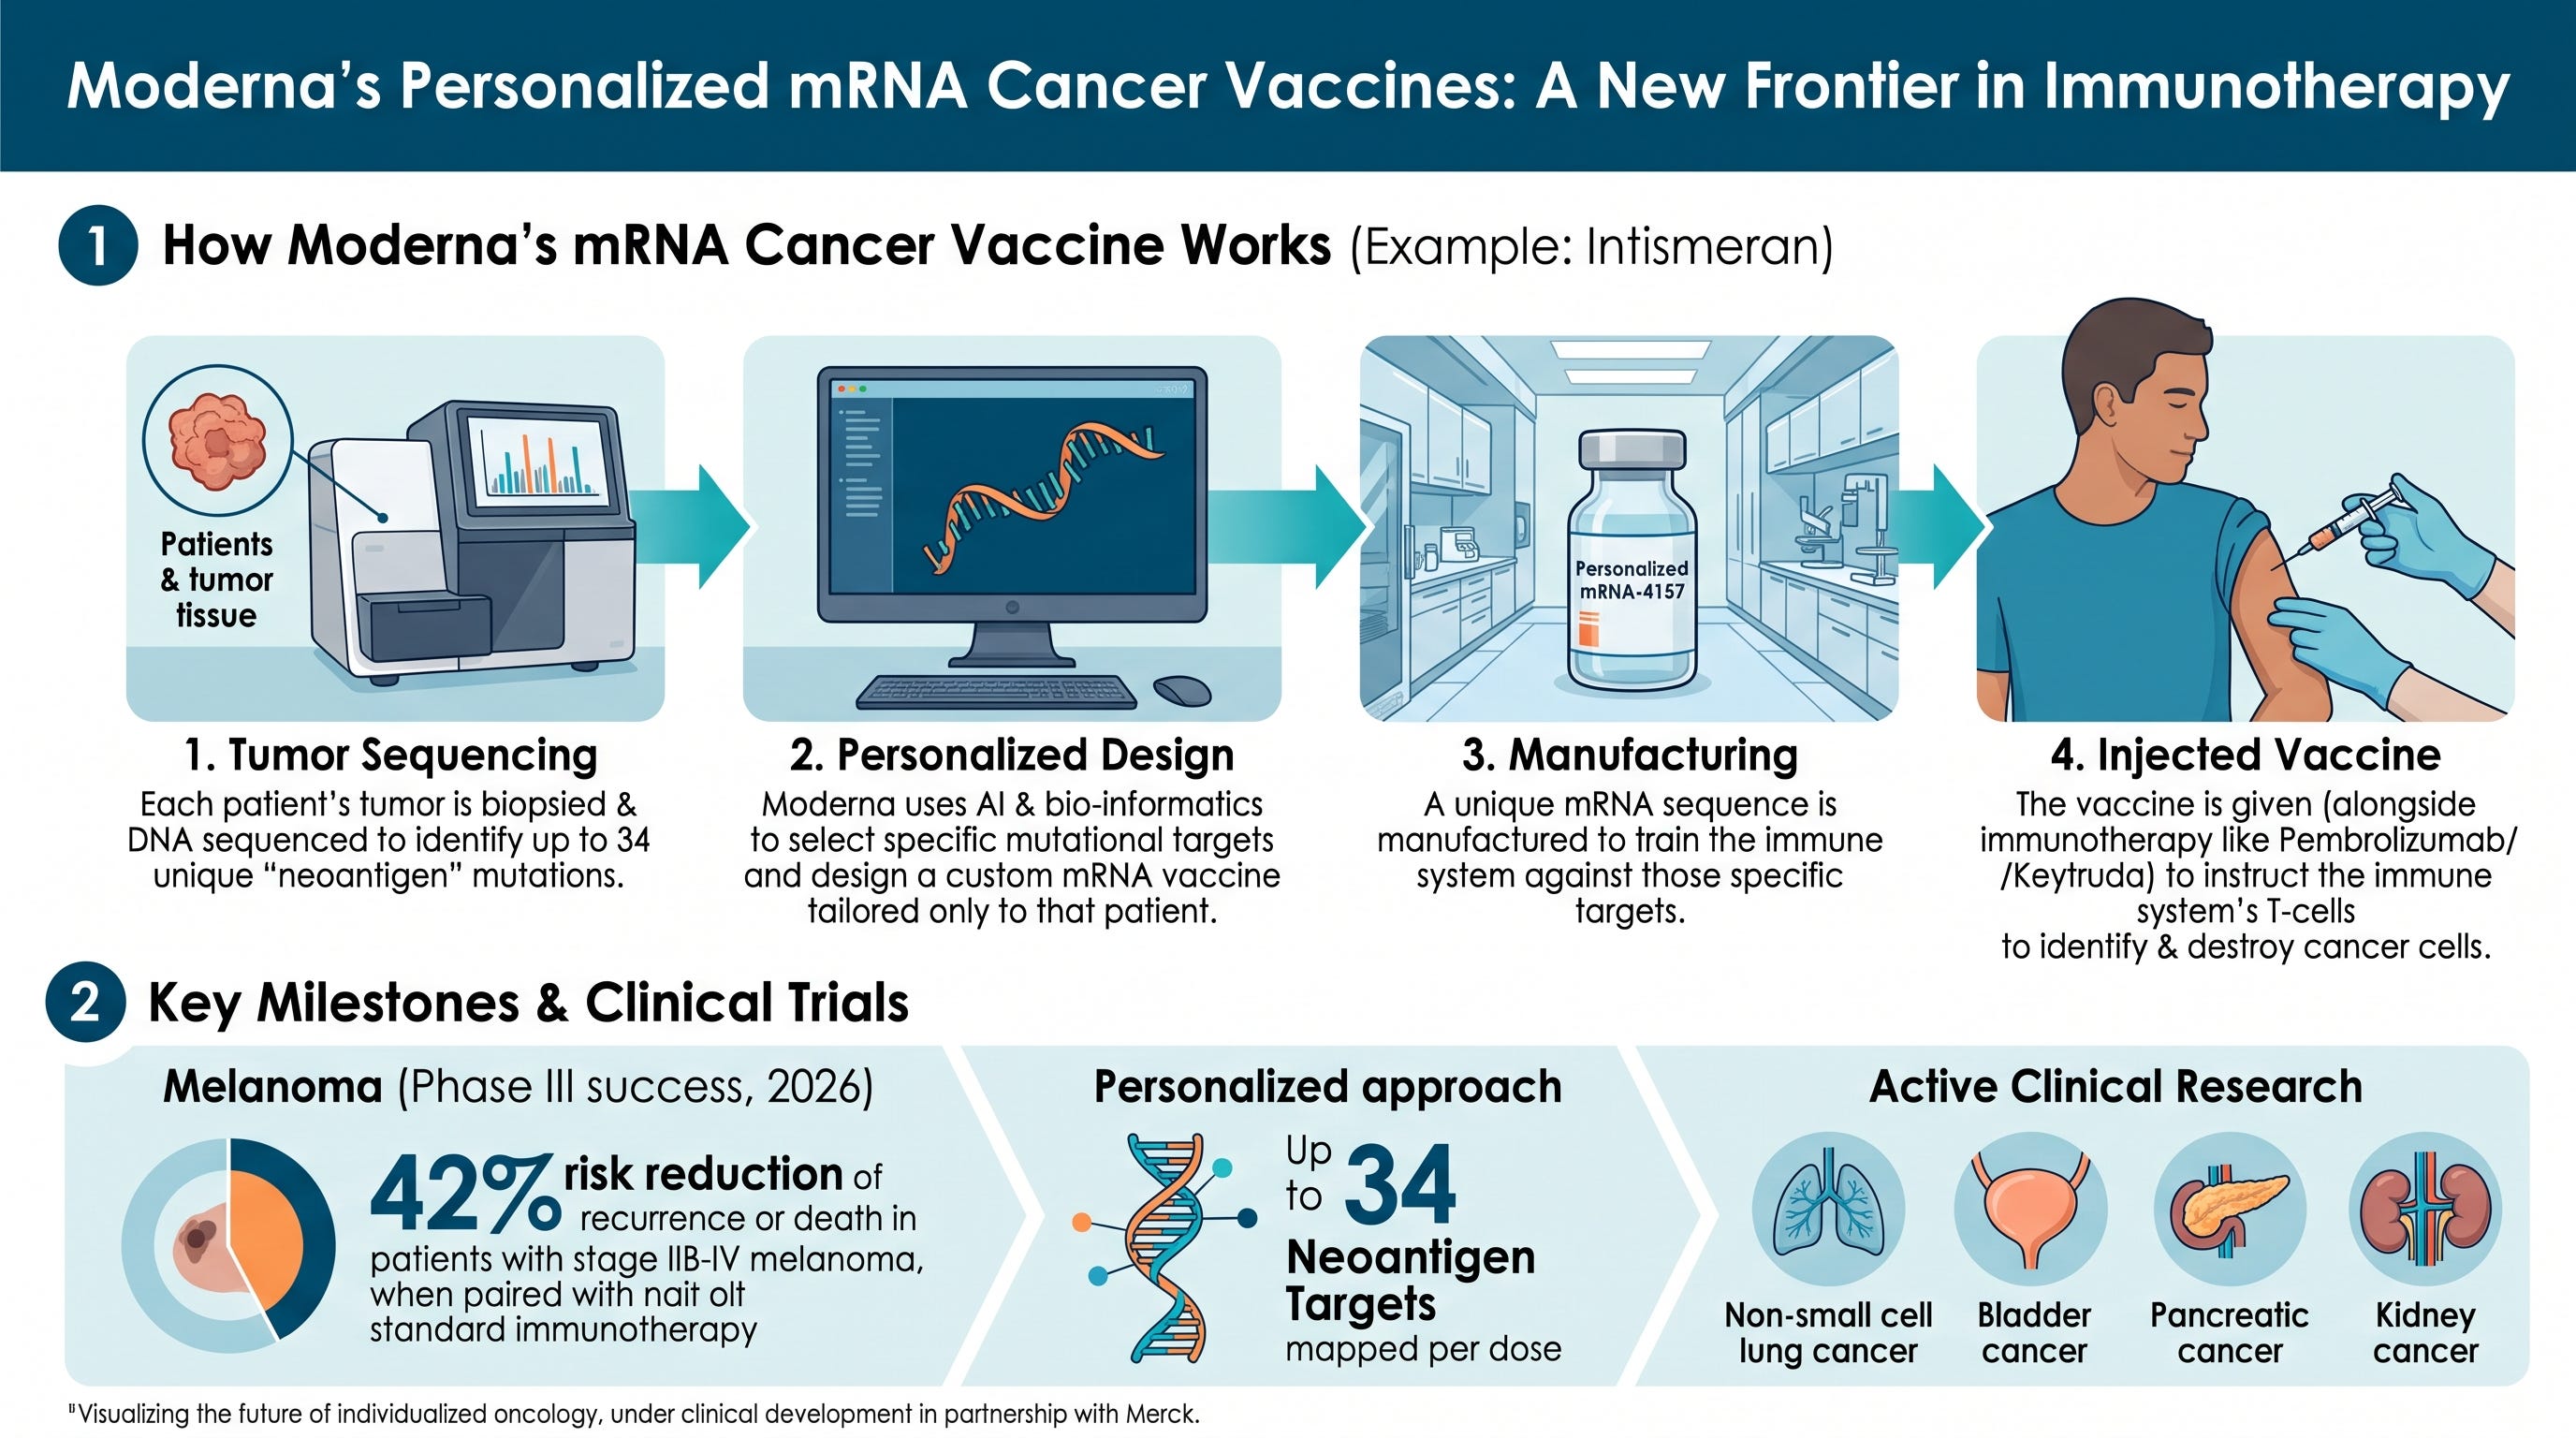
A cancer therapeutic vaccine is something you give to a person who already has cancer. The HPV vaccine and Hep B vax might prevent cancer but the melanoma vaccine is for folks who already have melanoma.
mRNA is just a novel way for the body to express the antigen.
Melanoma is a unique cancer. It is exquisitely sensitive to the immune system. It is one of 2 cancers where IL2 therapy improves outcomes and a cancer where Pembrolizumab has the greatest response. It is the only cancer with a TIL approval.
Part of the reason Moderna’s stock rose, and then fell upon release of the trial’s hazard ratio, and then rose again is because analysts are trying to make sense of a key question: is the success in melanoma a 1 off, or will this extend to all tumors.
I was surprised to read the New England Journal editorial that went even further.

The author speculates that a future vaccine might work as a preventive cancer vaccine— by stimulating the body to fight the most common cancer mutations, a future vaccine might prevent cancer before it starts.
That's a bold idea. It is far further than what most industry analysts are anticipating. One fact that works against this hypothesis is emerging evidence that non cancerous tissue have many of these very same mutations— particularly as we get older— thus such a preventive vaccine might stimulate a robust and nonspecific immune response against not-yet-cancer tissue. It's also unclear at what age it will be given. How many times it will be given. Additionally, whatever lessons come from Lynch syndrome may not be extrapolated to all people. In fact, in 2026, the idea feels more like science fiction than reality. But the truth is: no one knows for sure. Only future trials can tell us. I find it fascinating however when NEJM editorialists offer a more bullish case than even the most aggressive biotech analysts.
In the near term, we will get the results for additional mRNA vaccine trials in lung cancer and kidney cancer. If these are negative, then I suspect Moderna stock will sink further, and many analysts and experts will believe that the success in melanoma was unique. Already there is likely a far cheaper way to present the body with the antigens in melanoma— which is to cut it out after you give pembro (neoadjuvant approach) which appears to have a similar hazard ratio as moderna’s product.
If other tumor types have positive trial, we will likely see yet additional studies in places like pancreas, breast and colon cancer. Historically, these have been places where immunotherapy has had the least impact.
Alexander Pope said Hope Springs Eternal… and centuries later that remains the case. Yet I am always reminded of another saying: in God we trust, but all else should bring data.
mRNA? No thank you. As far as I'm concerned, you would have to be brain dead before taking anything that is based on mRNA. Fool me once, shame on you. Fool me twice, and I'm dead.
NEVER AGAIN.
Important context, Vinay, before comparing hazard ratios: these trials enrolled very different populations. Nearly a third of the vaccine trial patients had stage II melanoma, and many had stage III microscopic nodal disease. Neither group would have qualified for S1801 or NADINA, which required clinically detectable disease. So many of these patients would not have qualified for neoadjuvant immunotherapy.