

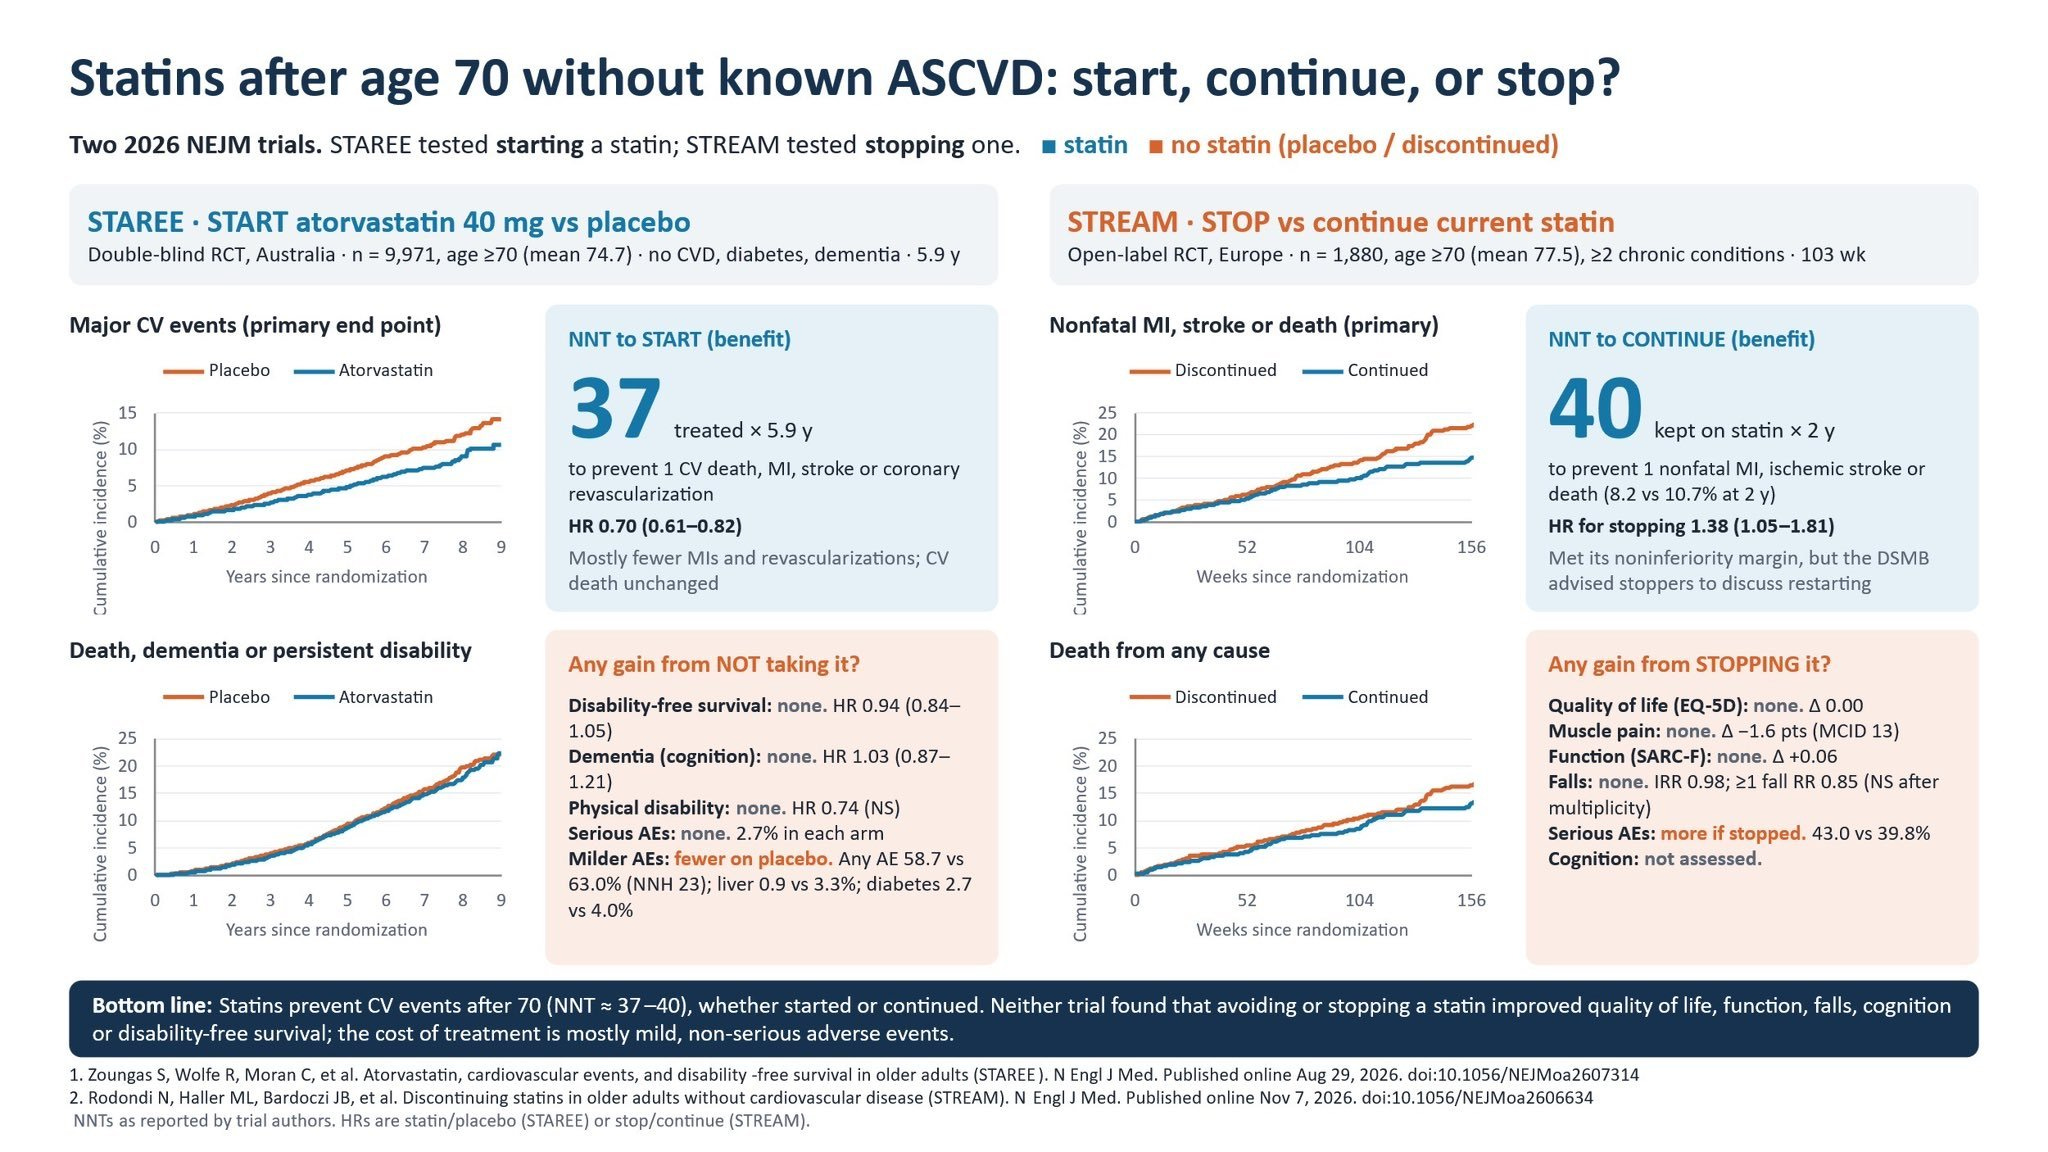
(At least) two recent randomized trials directly address the question of whether older individuals should take a statin. One is a superiority trial, and the other non-inferiority. Both are remarkably consistent, and highlight how this decision is highly preference sensitive.
First, consider that we are talking about people who make it to the age of 70 without having had a heart attack, stroke, or otherwise diagnosed with coronary artery disease or peripheral arterial disease. In other words, this is a primary prevention (and not secondary prevention) population.
Next, as we get older in life, competing risks rise. Although we still want to avoid dying of cardiovascular disease, the risk of dying of something—including cancer— grows.
Staree shows that starting a statin has a reduction in non-fatal mi, stroke or coronary revasc, and Stream shows that continuing a statin is better than discontinuing for the endpoint of nonfatal MI, stroke, or death. It means little that the trial was technically non-inferior, when the non-inferiority margin is so big you can parallel park a school bus in it.
Meanwhile, because competing risk is high, we don’t see a convincing signal of all-cause mortality benefit.
What should you do? I think different people can look at these data and decide differently. Some people want to do anything to avoid even the slightest risk of a bad outcome— even if the benefits are extremely slim. While others don’t want to take a pill (want to avoid medicalization) even for substantial gains. I can imagine some want a statin, others don’t and a tiny fraction would make their decision based on these data.
Do we need another statins trial in the elderly? There is a 90 million dollar taxpayer supported effort called PREVENTABLE, but if you ask me, this is a a misuse of taxpayer money. The value of information— potential for this trial to change how people vote with their feet— is very low. Meanwhile, there are many other societal priorities we could do with 90 million.
What do you think? Looking at these 2 trials what would you do if you were 70 and without pre-existing CV disease?
Almost 70yo newly retired ophthalmologist. Never smoker. Currently walking 4-5 mi/day and lifting wts for 1 hr 3x/wk. Cholesterol 269 (always high). HDL 101(115 and 106 previous 2 years with ratio 2.7, but even when I was running marathons it was high in my 30's and 40's. Seems to be familial as sisters have the same and mother did. Father's side CV risks for sure though. Paternal gm died of CVA and perhaps gf). PCP was going to put me on statin but we did coronary calcium scan and it was zero 3 yrs ago. I do have some plaque in one carotid per am U/S done in his office a few yrs ago. 70 doesn't feel old to me and I don't want to live my retirement with a stroke so what do you think??? I may be repeating my carotid U/S...not sure how good an office one is though without a radiologist.